

How Neurontin Works: Mechanisms Behind Anxiety Relief
Imagine a patient noticing that racing thoughts soften after starting gabapentin. The drug targets the neuronal α2δ subunit on presynaptic voltage gated calcium channels, reducing calcium influx and lowering release of excitatory neurotransmitters. That cascade can diminish amygdala hyperactivity that feeds excessive worry and panic.
Rather than binding GABA-A sites, it indirectly shifts inhibitory tone and modulates synaptic plasticity. By decreasing glutamate and substance P release, gabapentin reduces neuronal hyperexcitability and eases physiological arousal linked to anxiety. Effects on sleep and pain pathways may contribute to perceived relief.
Mechanistic certainty remains limited, and responses vary across individuals and trials. Occassionally benefit appears after weeks, and dose, comorbidity and enviroment influence outcomes. Clinicians should frame use as a targeted trial with measurable goals, monitoring effects and side effects to decide whether potential gains outweigh risks. Shared decision making is essential always.
| Mechanism | Effect |
|---|---|
| α2δ subunit binding | ↓ presynaptic Ca2+ influx |
| Reduced glutamate release | ↓ amygdala excitability |
Clinical Evidence: Studies Supporting Gabapentin Use
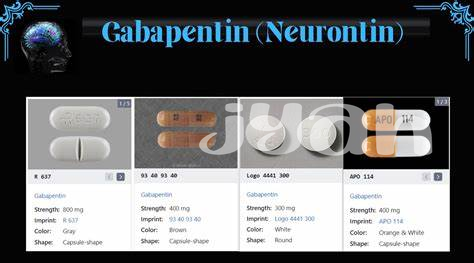
Randomized trials and meta-analyses have probed neurontin’s potential for anxiety, showing modest reductions in symptom scores and improved sleep in some cohorts.
Open-label studies and case series suggest benefit in social anxiety and alcohol-related anxiety, but sample sizes were small and follow-up short.
A few placebo-controlled trials found significant improvements, yet others failed to separate effect from placebo, creating a mixed evidence base.
Clinicians Definately weigh these findings against safety data and individual patient factors when considering neurontin as an off-label option. More robust trials are still urgently needed now.
Conflicting Trials: What the Research Still Misses
Conflicting trial results leave clinicians in a gray zone, where promising case series and small RCTs suggest benefit but larger studies are inconsistent. Patients report real relief on neurontin, yet methodological gaps — small samples, short follow-up, variable dosing — limit confident conclusions.
Researchers also lack clarity on long-term outcomes, withdrawal effects, and interactions with concomitant psychiatric meds. Untill robust multicenter trials and independent meta-analyses fill these gaps, use remains driven by clinical judgement, patient preference, and practical access considerations for patient safety, and cautious monitoring rather than definitive evidence.
Safety Concerns: Side Effects, Dependence, Overdose Risks

Patients often report drowsiness, dizziness, and cognitive blunting after starting neurontin; these side effects can be mild at first but interfere with work or driving, and are Occassionally persistent rather than transient.
Dependence is debated: some people develop tolerance and experience withdrawal symptoms when stopping, whereas others tolerate the drug well; combining with alcohol or opioids elevates respiratory depression and overdose risk, so prescribers should screen and counsel.
Clinicians must weigh potential benefit against harm, monitor closely for signs of misuse, and Aquire baseline kidney function and fall-risk assessments in older adults; shared decision-making and slow tapering plans help reduce adverse outcomes. Patients should report suicidal thoughts or breathing problems immediately to clinicians or family.
Off-label Prescribing Trends and Regulatory Scrutiny
Clinicians and patients share stories of neurontin easing anxious nights, yet prescribing patterns reveal wider use beyond approved indications. Some doctors embrace it; others question evidence still.
Policy makers and the Goverment have raised flags about rapid off-label expansion, prompting reviews.
Debate mixes patient need with concerns about marketing and insufficient trials. Until clearer consensus emerges, clinicians should weigh benefits, document rationale, and follow patients closely to spot side effects or misuse.
| Metric | Note |
|---|---|
| Use | Off-label |
Practical Guidance: When Gabapentin Might Be Considered
In clinical practice, gabapentin may be considered when first-line therapies like SSRIs and cognitive-behavioral therapy produce partial response, or when anxiety overlaps with neuropathic pain, insomnia, or alcohol withdrawal. Start low and titrate slowly, monitor renal function, and set clear, realistic goals: benefits are often modest and evidence remains mixed.
Shared decision making is key: review prior treatment, substance use, fall risk, and comorbidities. Consider a predefined four to eight week trial with outcome measures and a plan to stop if there is no meaningful improvement. Counsel about side effects, dependence risk and rare misuse; adjust dosing for renal impairment and involve specialists when care is complex. Occassionally neccessary to document monitoring and track progress. MedlinePlus: Gabapentin Review: Gabapentin (PMC)